4.3% per year: what happens to untreated varicose veins
Whiteley's review brings together what is known about the varicose veins left untreated: an annual rate of deterioration by stage CEAP, a randomized trial in which compression lost in quality of life, and the line that separates medical indication of aesthetic service.
 View the video lesson
The question the patient asks and rarely receives a numerical answer is "what if I don't?". Whiteley's review responds with a number, defines what it means to worsen and shows why, in the author's reading, compression medium and venotonic do not occupy the place of treatment.
The annual rate of deterioration

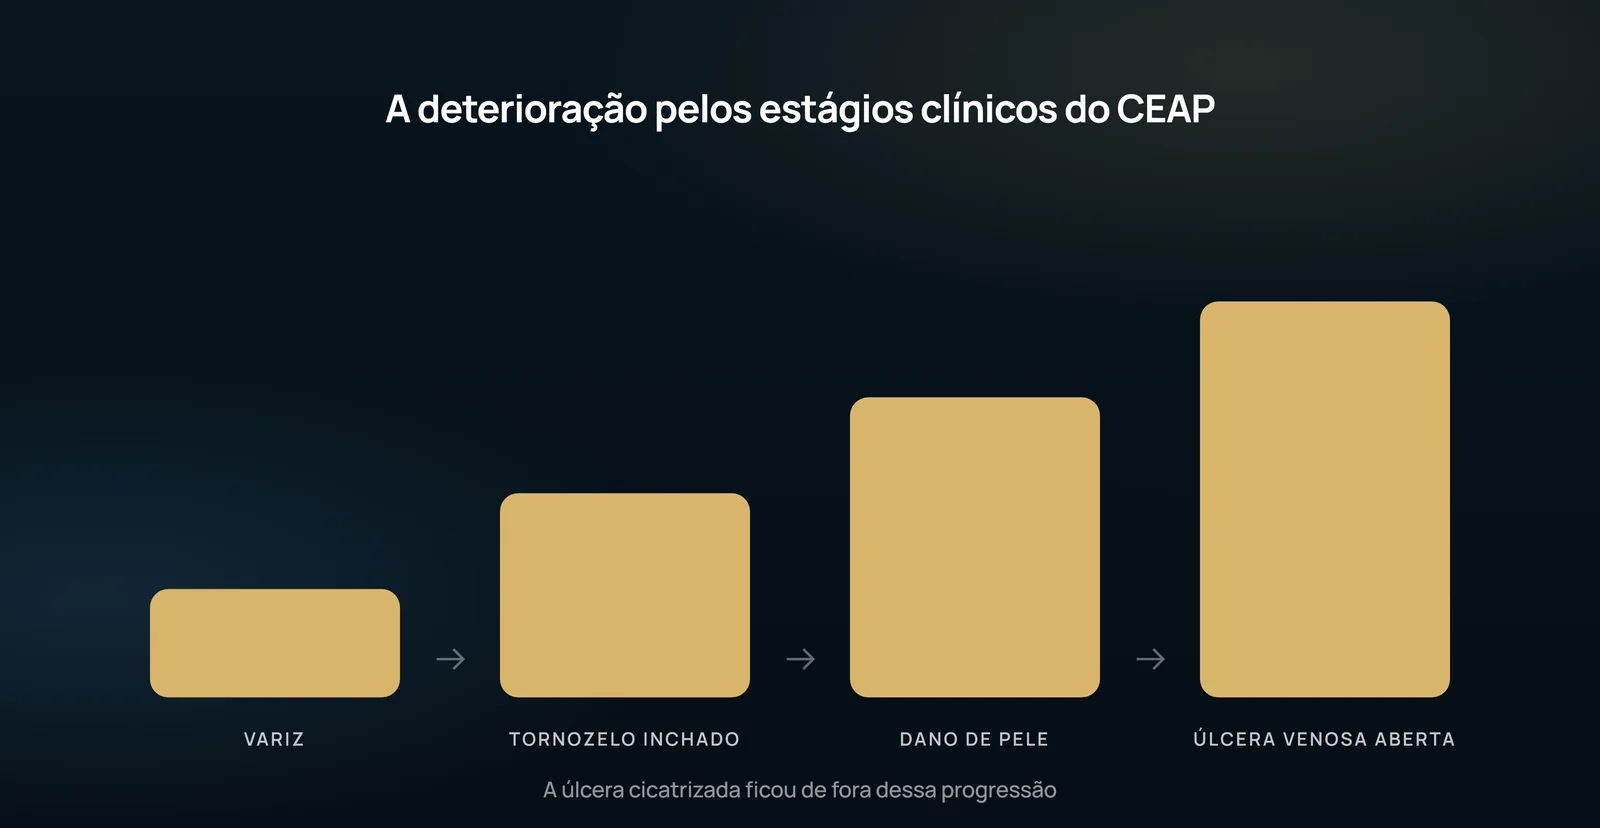
Deterioration was defined by clinical stages of CEAP: C2, varicose veins; C3, swollen ankles; C4, skin damage — venous eczema or hemosiderin; and C6, venous leg ulcer. C5, healed venous ulcer, is not part of this progression because it is not a next stage. The list of what untreated disease can produce also includes superficial venous thrombosis and bleeding from varicose veins.
The REACTIV test
REACTIV randomized patients between the best clinical treatment — graded compression stockings — and varicose veins treatment. Patients allocated to compression had worse quality of life after two years. The detail that changes reading is that the treatment arm was stripping surgery; the author himself comments that, with modern outpatient intravenous techniques, the advantage in quality of life would probably appear much earlier — which is his hypothesis, not measured from the trial.
Compression and venotonic in the right place
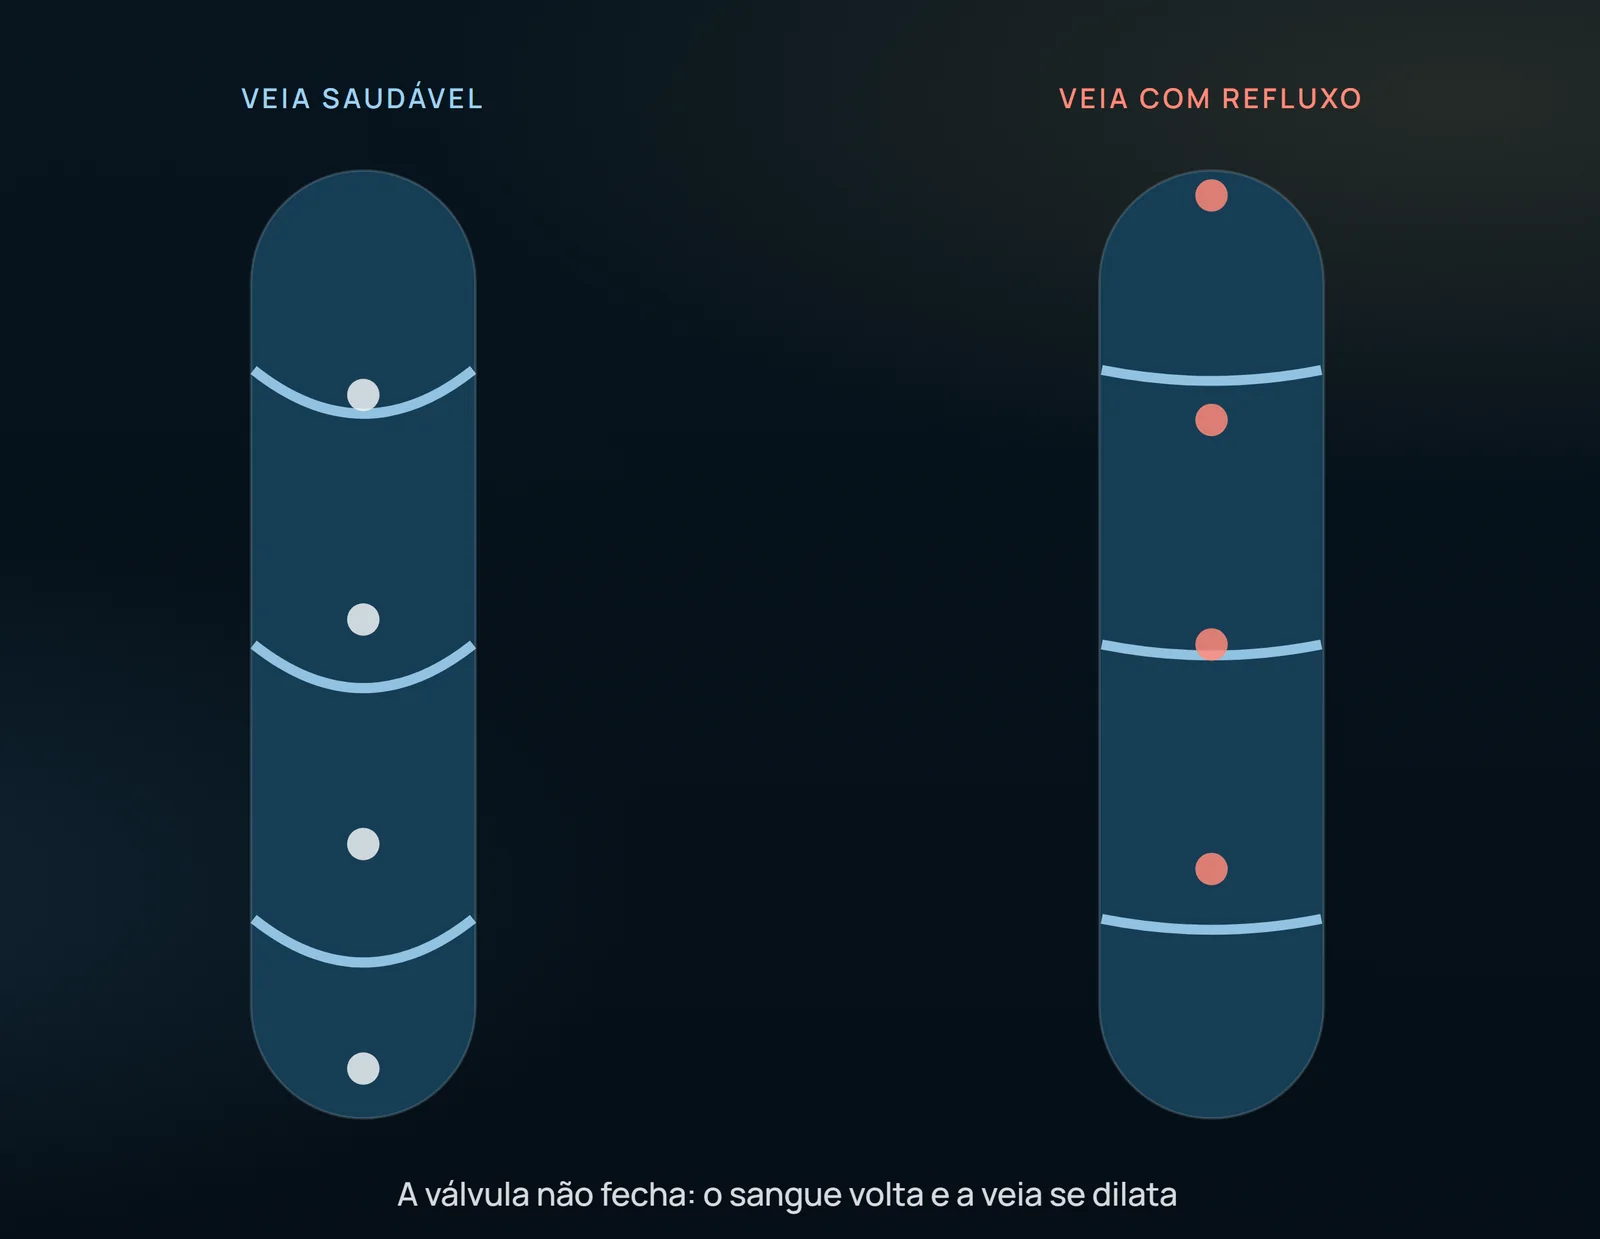
Gradual compression medium reduces reflux while being used; removal, reflux returns. Therefore, in the author's reading, there is no justification to recommend it as treatment of varicose veins, except when the patient cannot or does not want a curative intervention. The legitimate exception is the varicose veins secondary to postthrombotic syndrome or deep venous insufficiency, when the treated condition is not varicose veins. Venotropics, such as the purified micronized flavonoid fraction, reduce symptoms and edema of chronic venous insufficiency, but do not treat the underlying reflux — temporary relief without curative paper.
Hence a direct operational criticism: there is no logic in requiring the use of sock for a period before releasing treatment, to see if symptoms improve. This strategy only delays research and treatment — and it is because of this delay, the author writes, that health financiers often insist on the compression test.
Who to investigate and treat
In July 2013, NICE published the clinical guideline CG 168. Patient with bleeding varicose veins should be referred immediately. Patients with varicose veins — or suspected of hidden varicose veins — and any of these findings should be referred to a vascular service: primary or recurrent varicose veins with symptoms defined as pain, throbbing, discomfort, swelling, weight and itching; eczema or pigmentation of the lower leg; superficial venous thrombosis; venous leg ulcer; or healed venous ulcer.
The line between medical indication and aesthetic service
Patients without symptoms or signs of venous disease, besides visible veins, can be investigated and treated as long as the doctor is aware that he provides an aesthetic service, and does not treat a medical condition. Consent needs to reflect this, because it is not offering medical advantage and because an adverse result will generate concern. Still there is a technical floor: in the light of the published literature, treating leg telangiectasis without preoperative evaluation with duplex looking for reflux is, in the author's words, probably indefensible — most have underlying reflux of saphenous, perforating or local veins that feed telangiectasis.
What this article does not allow to say
This is a narrative review of a single author, not a systematic review or an essay: there is no declared search protocol or comparator arm. The rate of 4.3% per year comes from a review of observational epidemiological studies and describes the average cohorts — it does not predict the course of a specific patient, nor does it allow to tell anyone in which year he will have an ulcer. REACTIV compared compression with stripping, so the superiority demonstrated is not that of current intravenous techniques. The aforementioned directive is British and organizes referral within that health system. Finally, the author declares to be the founder of the College of Phlebology, whose venous record he recommends making mandatory — a conflict that is contained in the article’s own disclosure section and which the reader should weigh when reading the practice recommendations.
Content addressed exclusively to health professionals. No individual result is guaranteed: the indication depends on clinical evaluation and imaging examination of each patient (CFM 2,336/2023).